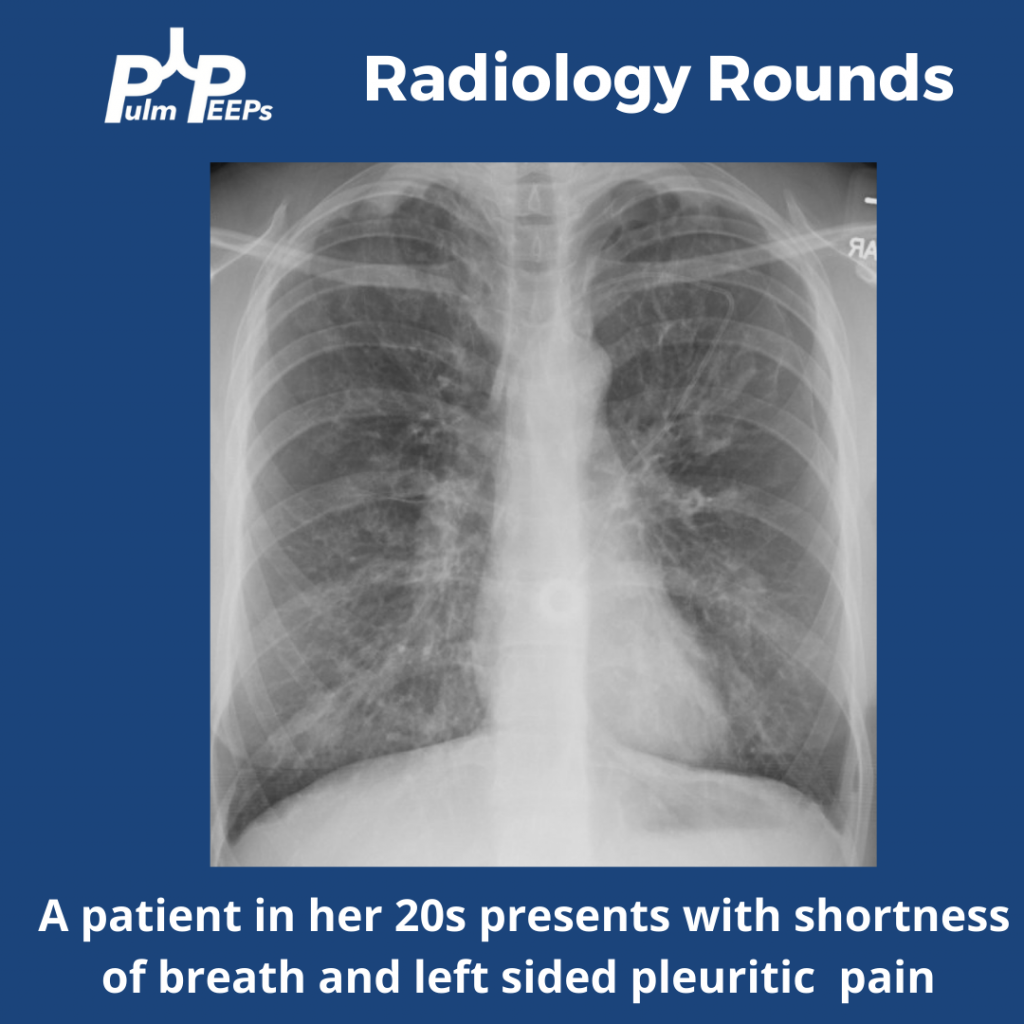
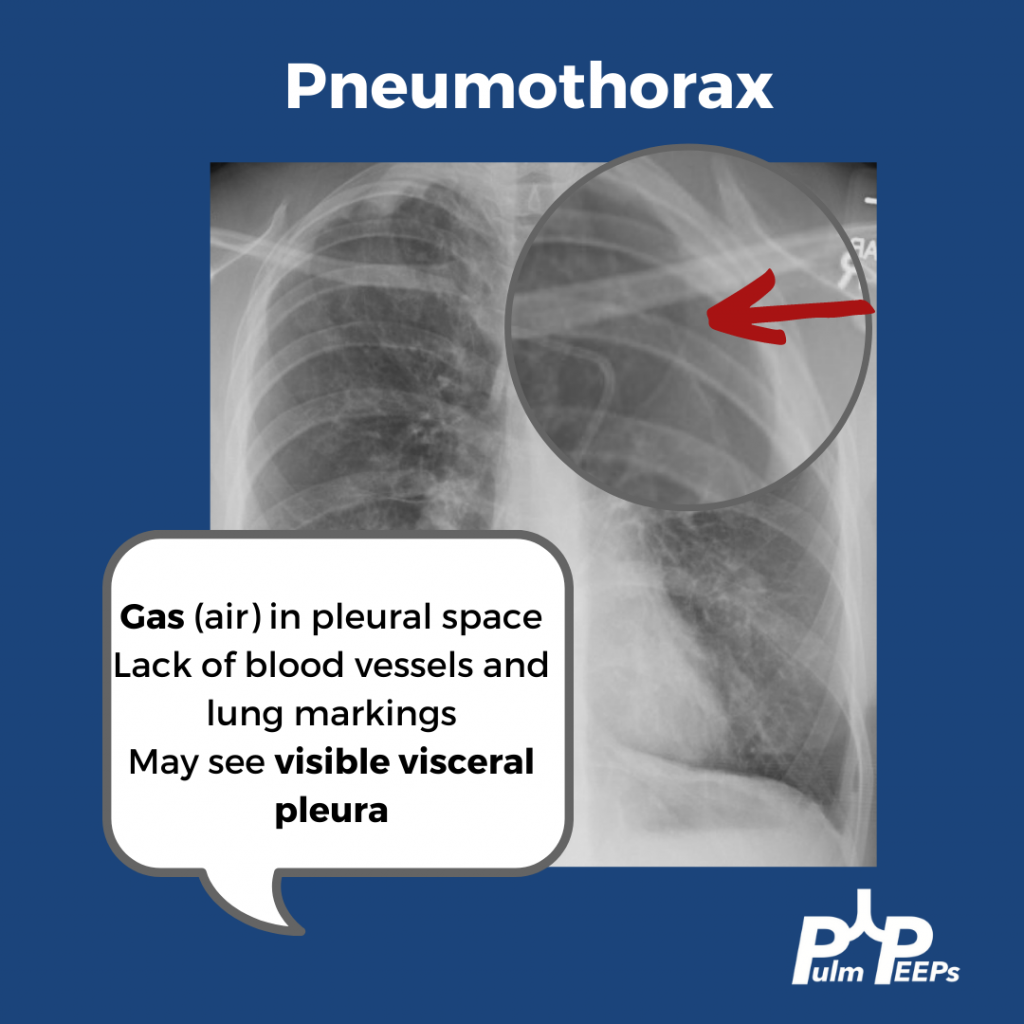
We’re back with another collaborative episode with BMJ Thorax. Episode 126 of Pulm PEEPs is our first Journal Club with BMJ Thorax devoted entirely to pleural disease. We’re joined by Thorax education editor Dr. Christopher Turnbull and Dr. Olivia Walsh of the Oxford Pleural Unit, author of the April 2026 Thorax Journal Club. Together we discuss four papers that span the pleural pathway: whether medical thoracoscopy needs an artificial pneumothorax, a new score to predict when a malignant pleural effusion will come back, how the first procedure in pleural infection shapes what happens next, and why a trial of early thoracoscopy for pleural infection couldn’t get off the ground.
Reading and appraising the literature is a core skill for every learner in pulmonary and critical care medicine. Our ongoing partnership with BMJ Thorax brings the authors of the Thorax Journal Club onto the show to walk through the papers they chose, how the studies were designed, and what they should (and shouldn’t) change at the bedside.
Meet Our Guests
Dr. Christopher Turnbull is a respiratory consultant and honorary researcher at Oxford University Hospitals, and the associate editor for education at Thorax. His work focuses on sleep-related breathing disorders. This is Chris’s fifth time on Pulm PEEPs, where he continues to be our go-to guide for methods and statistics.
Dr. Olivia Walsh is a pleural research fellow at the Oxford Pleural Unit, Oxford University Hospitals NHS Trust, and the author of the April 2026 Thorax Journal Club. Her clinical and research focus is pleural disease, with a particular interest in using new technologies and imaging to improve patient journeys and patient-centred care. She is our first guest from the Oxford Pleural Unit.
Journal Club Papers
- Walsh O. Journal club. Thorax 2026;81:404.
- Wang K, et al. Medical thoracoscopy with vs without prior artificial pneumothorax for patients with minimal or absent pleural effusion. Chest 2026;169(1):269–279.
- Mishra EK, et al. Time to next procedure in patients with malignant pleural effusion undergoing aspiration: derivation and initial validation of the RED score. Thorax 2026.
- Gonnelli F, et al. Italian multicentre study on the management of pLeural infection and empyema: IMPLE study. Respiratory Research 2025;26:322.
- Bansal KR, et al. First-line medical thoracoscopy for pleural infection: the SPIRIT randomised controlled feasibility trial. BMJ Open Respir Res 2025;12:e003675.
Interested in writing a Thorax Journal Club? Reach out to the Thorax education editor, and follow Thorax on social media to keep up with each month’s journal club.
Key Learning Points
1. Medical thoracoscopy with vs. without artificial pneumothorax (Wang et al, Chest 2026)
- Question: when there is little or no fluid, guidelines suggest inducing an artificial pneumothorax (AP) to create a working space. Is that extra step needed?
- Design: multicentre randomised non-inferiority trial at 6 hospitals in China (2021–2023). 204 adults with undiagnosed pleural disease and minimal (≤ 3 cm depth seated) or no effusion, randomised 1:1 to AP or non-AP. Primary outcome: pleural access success, with a non-inferiority margin of −10% set by expert consensus. Patients with complete pleural adhesions were excluded.
- Results: pleural access success 95.0% without AP vs. 78.4% with AP, so non-AP was non-inferior (and numerically better). Operation time was shorter without AP (32 vs. 40 min). Complications (14.9% vs. 17.6%) and pathological confirmation (76% vs. 75%) were similar.
- Why it matters: an artificial pneumothorax adds time, skill and risk. In the wrong patient, a prolonged air leak and a long stay with a chest drain can consume precious weeks for someone with limited life expectancy.
- Cautions: how the −10% margin was derived is not described in detail (Chris would like to see an international consensus, such as an eDelphi). All centres were in China, so procedural differences from UK and US practice need to be understood. The findings may not apply to patients with extensive adhesions or a complex pleural space.
- Take: food for thought rather than practice-changing. It supports the selective, patient-specific use of AP that many pleural teams already practise.
2. Predicting reaccumulation in malignant pleural effusion: the RED score (Mishra et al, Thorax 2026)
- Question: after therapeutic aspiration, can we predict who will need another pleural procedure, and how soon?
- Design: prospective observational cohort across 10 UK hospitals. 241 patients with known or suspected malignant pleural effusion undergoing therapeutic aspiration (derivation cohort n = 180), followed for 3 months. Outcome: time to next clinically indicated pleural procedure, grouped as fast (1–13 days), moderate (14–42 days) or slow (> 42 days or none). Initial validation in two external cohorts (n = 31 and n = 57).
- The score: three bedside variables, Respiratory rate (≥ 22 breaths/min), Effusion depth on ultrasound and Dyspnoea on a visual analogue scale.
- Results: higher RED scores → shorter time to the next procedure. Models had areas under the curve of 0.73–0.75 with acceptable calibration.
- At the bedside: calculate the score at the first aspiration. A high score → earlier clinic follow-up and an earlier conversation about definitive management (indwelling pleural catheter, or chest drain with talc) rather than repeated aspirations. A low score → a more conservative approach may be reasonable.
- Cautions: an AUC around 0.75 means moderate discrimination. The score adds structure to prognostic conversations but can’t tell an individual patient for certain whether they will need another procedure. It needs prospective validation before routine use.
- Next step (Chris): a trial in high-RED-score patients randomising an upfront indwelling pleural catheter vs. repeated aspiration.
3. Real-world procedural pathways in pleural infection: the IMPLE study (Gonnelli et al, Respiratory Research 2025)
- Question: does the first procedure we choose in pleural infection shape what happens next?
- Cohort: retrospective multicentre study of 509 adults hospitalised with stage 2–3 pleural infection or empyema at 14 Italian centres (2015–2021). First-line approach: chest drain 43%, medical thoracoscopy (MT) 24%, upfront surgery 13%, thoracentesis 11%. Models were adjusted for age, RAPID score and number of comorbidities.
- Results:
- Subsequent surgical referral: thoracentesis (OR 6.0) and chest drain (OR 7.8) first ↑ the odds compared with MT first.
- Length of stay: chest drain (+4.9 days) and upfront surgery (+5.2 days) ↑ compared with MT.
- Intervention within 24 hours → shorter stay, whatever the procedure. Timing may matter as much as the type.
- No difference in 90-day mortality. The differences are in morbidity and resource use, not survival.
- Larger-bore drains and baseline loculations/septations were associated with more surgical referral.
- Interpretation cautions: observational data with likely unmeasured confounding. Clinicians may choose thoracentesis for frailer patients and reserve MT, which requires a fairly robust patient, for those with more physiological reserve. Correlation does not imply causation.
- Take: it doesn’t change practice overnight, but it is a reason to pause before defaulting to the stepwise approach and to consider earlier definitive intervention. MIST-4, a large multicentre RCT of early surgery vs. early intrapleural enzyme therapy led from Oxford, is about to start.
4. First-line medical thoracoscopy for pleural infection: the SPIRIT feasibility trial (Bansal et al, BMJ Open Respir Res 2025)
- Question: is a full-scale RCT of early MT vs. chest drain for pleural infection deliverable in the NHS?
- Design: open-label randomised feasibility trial at 7 NHS centres (2017–2019). Adults with suspected pleural infection were randomised to a chest drain or MT on the same or next day, with 90-day follow-up. The primary outcome was feasibility (prescreening, screening and allocation failure), not a clinical endpoint.
- Results: of 193 patients prescreened, 181 (93.8%) were excluded and only 12 were randomised, so the feasibility endpoint was not met. The main reasons were no MT available in time (49%), an effusion that wasn’t truly infected (45%) and contraindications (44%). MT took about 15 minutes longer. Drains stayed in more than 3 days longer in the control arm, but no clinical differences were significant, and the trial was never powered to show them.
- Interpretation: a failure of the system, not of the question. Most pulmonologists are trained to place a chest drain, but few are trained in MT, and pleural infection tends to arrive after 5 p.m., seven days a week, not when a pleural list is running.
- How Chris would redesign it: start in a single centre with many trained operators and a seven-day emergency list, get the pathway right there, and then scale it up, much as primary PCI replaced thrombolysis once the evidence and the cath lab infrastructure caught up.
Practical Takeaways for the Pleural Service
- Use artificial pneumothorax selectively. In patients with minimal or no fluid and no extensive adhesions, a non-AP approach may be just as successful and quicker.
- Put a number on reaccumulation. Respiratory rate, effusion depth and breathlessness at the first aspiration can flag patients who need early follow-up and an early discussion of an IPC or talc.
- The first procedure in pleural infection matters. Choose it deliberately and early, not just the default chest drain.
- Measure what matters to patients: quality of life and symptoms, not only fluid volume and radiology.
- Be pragmatic. Adapt the evidence to what your own system can realistically deliver.
Research/Implementation Gaps Highlighted
- An internationally agreed non-inferiority margin for thoracoscopic access, and trials outside China.
- Prospective external validation of the RED score, and a trial of risk-guided definitive management.
- Randomised data on first-line MT or early surgery in pleural infection (MIST-4 is about to start).
- Service redesign (training, emergency thoracoscopy capacity) before a definitive MT trial is feasible in the NHS.
Pro Tip from the Episode
A non-inferiority trial asks whether a new approach is not worse than the standard by more than a prespecified margin, not whether it is better. To read one, find the margin and ask whether it is clinically sensible and how it was chosen. Then check the confidence interval for the difference: if its lower bound stays above the margin, non-inferiority is shown. And for every observational study, remember Chris’s parting reminder: correlation does not imply causation.