126. Pleural Journal Club with BMJ Thorax

Cover Images

We’re back with another collaborative episode with BMJ Thorax. Episode 126 of Pulm PEEPs is our first Journal Club with BMJ Thorax devoted entirely to pleural disease. We’re joined by Thorax education editor Dr. Christopher Turnbull and Dr. Olivia Walsh of the Oxford Pleural Unit, author of the April 2026 Thorax Journal Club. Together we discuss four papers that span the pleural pathway: whether medical thoracoscopy needs an artificial pneumothorax, a new score to predict when a malignant pleural effusion will come back, how the first procedure in pleural infection shapes what happens next, and why a trial of early thoracoscopy for pleural infection couldn’t get off the ground.

Reading and appraising the literature is a core skill for every learner in pulmonary and critical care medicine. Our ongoing partnership with BMJ Thorax brings the authors of the Thorax Journal Club onto the show to walk through the papers they chose, how the studies were designed, and what they should (and shouldn’t) change at the bedside.

Dr. Christopher Turnbull is a respiratory consultant and honorary researcher at Oxford University Hospitals, and the associate editor for education at Thorax. His work focuses on sleep-related breathing disorders. This is Chris’s fifth time on Pulm PEEPs, where he continues to be our go-to guide for methods and statistics.

Dr. Olivia Walsh is a pleural research fellow at the Oxford Pleural Unit, Oxford University Hospitals NHS Trust, and the author of the April 2026 Thorax Journal Club. Her clinical and research focus is pleural disease, with a particular interest in using new technologies and imaging to improve patient journeys and patient-centred care. She is our first guest from the Oxford Pleural Unit.

Interested in writing a Thorax Journal Club? Reach out to the Thorax education editor, and follow Thorax on social media to keep up with each month’s journal club.

1. Medical thoracoscopy with vs. without artificial pneumothorax (Wang et al, Chest 2026)

  • Question: when there is little or no fluid, guidelines suggest inducing an artificial pneumothorax (AP) to create a working space. Is that extra step needed?
  • Design: multicentre randomised non-inferiority trial at 6 hospitals in China (2021–2023). 204 adults with undiagnosed pleural disease and minimal (≤ 3 cm depth seated) or no effusion, randomised 1:1 to AP or non-AP. Primary outcome: pleural access success, with a non-inferiority margin of −10% set by expert consensus. Patients with complete pleural adhesions were excluded.
  • Results: pleural access success 95.0% without AP vs. 78.4% with AP, so non-AP was non-inferior (and numerically better). Operation time was shorter without AP (32 vs. 40 min). Complications (14.9% vs. 17.6%) and pathological confirmation (76% vs. 75%) were similar.
  • Why it matters: an artificial pneumothorax adds time, skill and risk. In the wrong patient, a prolonged air leak and a long stay with a chest drain can consume precious weeks for someone with limited life expectancy.
  • Cautions: how the −10% margin was derived is not described in detail (Chris would like to see an international consensus, such as an eDelphi). All centres were in China, so procedural differences from UK and US practice need to be understood. The findings may not apply to patients with extensive adhesions or a complex pleural space.
  • Take: food for thought rather than practice-changing. It supports the selective, patient-specific use of AP that many pleural teams already practise.

2. Predicting reaccumulation in malignant pleural effusion: the RED score (Mishra et al, Thorax 2026)

  • Question: after therapeutic aspiration, can we predict who will need another pleural procedure, and how soon?
  • Design: prospective observational cohort across 10 UK hospitals. 241 patients with known or suspected malignant pleural effusion undergoing therapeutic aspiration (derivation cohort n = 180), followed for 3 months. Outcome: time to next clinically indicated pleural procedure, grouped as fast (1–13 days), moderate (14–42 days) or slow (> 42 days or none). Initial validation in two external cohorts (n = 31 and n = 57).
  • The score: three bedside variables, Respiratory rate (≥ 22 breaths/min), Effusion depth on ultrasound and Dyspnoea on a visual analogue scale.
  • Results: higher RED scores → shorter time to the next procedure. Models had areas under the curve of 0.73–0.75 with acceptable calibration.
  • At the bedside: calculate the score at the first aspiration. A high score → earlier clinic follow-up and an earlier conversation about definitive management (indwelling pleural catheter, or chest drain with talc) rather than repeated aspirations. A low score → a more conservative approach may be reasonable.
  • Cautions: an AUC around 0.75 means moderate discrimination. The score adds structure to prognostic conversations but can’t tell an individual patient for certain whether they will need another procedure. It needs prospective validation before routine use.
  • Next step (Chris): a trial in high-RED-score patients randomising an upfront indwelling pleural catheter vs. repeated aspiration.

3. Real-world procedural pathways in pleural infection: the IMPLE study (Gonnelli et al, Respiratory Research 2025)

  • Question: does the first procedure we choose in pleural infection shape what happens next?
  • Cohort: retrospective multicentre study of 509 adults hospitalised with stage 2–3 pleural infection or empyema at 14 Italian centres (2015–2021). First-line approach: chest drain 43%, medical thoracoscopy (MT) 24%, upfront surgery 13%, thoracentesis 11%. Models were adjusted for age, RAPID score and number of comorbidities.
  • Results:
    • Subsequent surgical referral: thoracentesis (OR 6.0) and chest drain (OR 7.8) first ↑ the odds compared with MT first.
    • Length of stay: chest drain (+4.9 days) and upfront surgery (+5.2 days) ↑ compared with MT.
    • Intervention within 24 hours → shorter stay, whatever the procedure. Timing may matter as much as the type.
    • No difference in 90-day mortality. The differences are in morbidity and resource use, not survival.
    • Larger-bore drains and baseline loculations/septations were associated with more surgical referral.
  • Interpretation cautions: observational data with likely unmeasured confounding. Clinicians may choose thoracentesis for frailer patients and reserve MT, which requires a fairly robust patient, for those with more physiological reserve. Correlation does not imply causation.
  • Take: it doesn’t change practice overnight, but it is a reason to pause before defaulting to the stepwise approach and to consider earlier definitive intervention. MIST-4, a large multicentre RCT of early surgery vs. early intrapleural enzyme therapy led from Oxford, is about to start.

4. First-line medical thoracoscopy for pleural infection: the SPIRIT feasibility trial (Bansal et al, BMJ Open Respir Res 2025)

  • Question: is a full-scale RCT of early MT vs. chest drain for pleural infection deliverable in the NHS?
  • Design: open-label randomised feasibility trial at 7 NHS centres (2017–2019). Adults with suspected pleural infection were randomised to a chest drain or MT on the same or next day, with 90-day follow-up. The primary outcome was feasibility (prescreening, screening and allocation failure), not a clinical endpoint.
  • Results: of 193 patients prescreened, 181 (93.8%) were excluded and only 12 were randomised, so the feasibility endpoint was not met. The main reasons were no MT available in time (49%), an effusion that wasn’t truly infected (45%) and contraindications (44%). MT took about 15 minutes longer. Drains stayed in more than 3 days longer in the control arm, but no clinical differences were significant, and the trial was never powered to show them.
  • Interpretation: a failure of the system, not of the question. Most pulmonologists are trained to place a chest drain, but few are trained in MT, and pleural infection tends to arrive after 5 p.m., seven days a week, not when a pleural list is running.
  • How Chris would redesign it: start in a single centre with many trained operators and a seven-day emergency list, get the pathway right there, and then scale it up, much as primary PCI replaced thrombolysis once the evidence and the cath lab infrastructure caught up.

Practical Takeaways for the Pleural Service

  • Use artificial pneumothorax selectively. In patients with minimal or no fluid and no extensive adhesions, a non-AP approach may be just as successful and quicker.
  • Put a number on reaccumulation. Respiratory rate, effusion depth and breathlessness at the first aspiration can flag patients who need early follow-up and an early discussion of an IPC or talc.
  • The first procedure in pleural infection matters. Choose it deliberately and early, not just the default chest drain.
  • Measure what matters to patients: quality of life and symptoms, not only fluid volume and radiology.
  • Be pragmatic. Adapt the evidence to what your own system can realistically deliver.

Research/Implementation Gaps Highlighted

  • An internationally agreed non-inferiority margin for thoracoscopic access, and trials outside China.
  • Prospective external validation of the RED score, and a trial of risk-guided definitive management.
  • Randomised data on first-line MT or early surgery in pleural infection (MIST-4 is about to start).
  • Service redesign (training, emergency thoracoscopy capacity) before a definitive MT trial is feasible in the NHS.

Pro Tip from the Episode

A non-inferiority trial asks whether a new approach is not worse than the standard by more than a prespecified margin, not whether it is better. To read one, find the margin and ask whether it is clinically sensible and how it was chosen. Then check the confidence interval for the difference: if its lower bound stays above the margin, non-inferiority is shown. And for every observational study, remember Chris’s parting reminder: correlation does not imply causation.
125. IVC Ultrasound and Volume Responsiveness

Should this patient get more fluid? It comes up on nearly every ICU shift, and the IVC is usually the first thing we scan to answer it. In this Pulm PEEPs Pearls episode, Furf and Monty cover how to get a reliable IVC view, how to read it in intubated and spontaneously breathing patients, the cutoffs worth knowing, what the data actually show, and the pitfalls that make the IVC mislead us.

Key Learning Points

Volume Responsiveness vs. Volume Status

“Volume status,” “volume depleted” and “fluid responsive” get used interchangeably on rounds, but they are not the same thing. Fluid responsiveness is a physiologic definition: a patient is fluid responsive if a fluid bolus (usually 250 to 500 mL) increases stroke volume or cardiac output by at least 10 to 15 percent. In Frank-Starling terms, you are asking whether both ventricles are still on the steep part of the curve.

Only about half of hemodynamically unstable ICU patients are fluid responsive. This has been shown again and again, going back to the classic Michard and Teboul review. If we bolus everyone who is hypotensive, roughly half get the downsides of fluid (edema, worse oxygenation, organ congestion) with none of the upside.

Responsive does not necessarily mean needs fluid. Most healthy people are fluid responsive. A patient can even be fluid responsive and volume overloaded at the same time. Responsiveness only tells you the heart can use more preload, so the decision always sits inside the clinical picture:

  • Is there hypoperfusion?
  • Is there reason to think low cardiac output is the problem?
  • Will the patient tolerate more fluid, especially from a lung standpoint?

Why Would the IVC Tell Us Anything?

The IVC is a thin-walled, compliant vessel sitting between the abdomen and the right atrium. Its size reflects the balance between right atrial pressure on one side and intra-abdominal pressure on the other. Breathing changes the pressures around it, and how the IVC responds depends entirely on whether the patient is breathing on their own or receiving positive pressure.

  • Spontaneously breathing: inspiration makes intrathoracic pressure negative, blood is pulled into the chest, and the IVC gets smaller. This is collapsibility.
  • Passively ventilated: each positive-pressure breath raises intrathoracic and right atrial pressure, impeding venous return, so the IVC gets bigger on inspiration. This is distensibility.

The theory: a patient on the flat part of the Frank-Starling curve has a high right atrial pressure and a full, stiff IVC that barely moves. A patient on the steep part has a lower right atrial pressure and a more compliant IVC that swings with each breath. Lots of respiratory variation suggests fluid responsiveness; very little suggests fluid will not help.

Quick bedside trick: take a deep breath yourself. Your chest expands, your diaphragm drops, intrathoracic pressure falls and your IVC empties into the right atrium. Positive pressure is the reverse.

Getting the Image

You cannot do this well without practice, so scan your patients routinely, not only when the stakes are high.

  • Probe and preset: phased array or curvilinear probe, with the abdominal or cardiac preset.
  • Position: patient supine. Head position matters a little, so keep it consistent if you plan to compare scans over time.
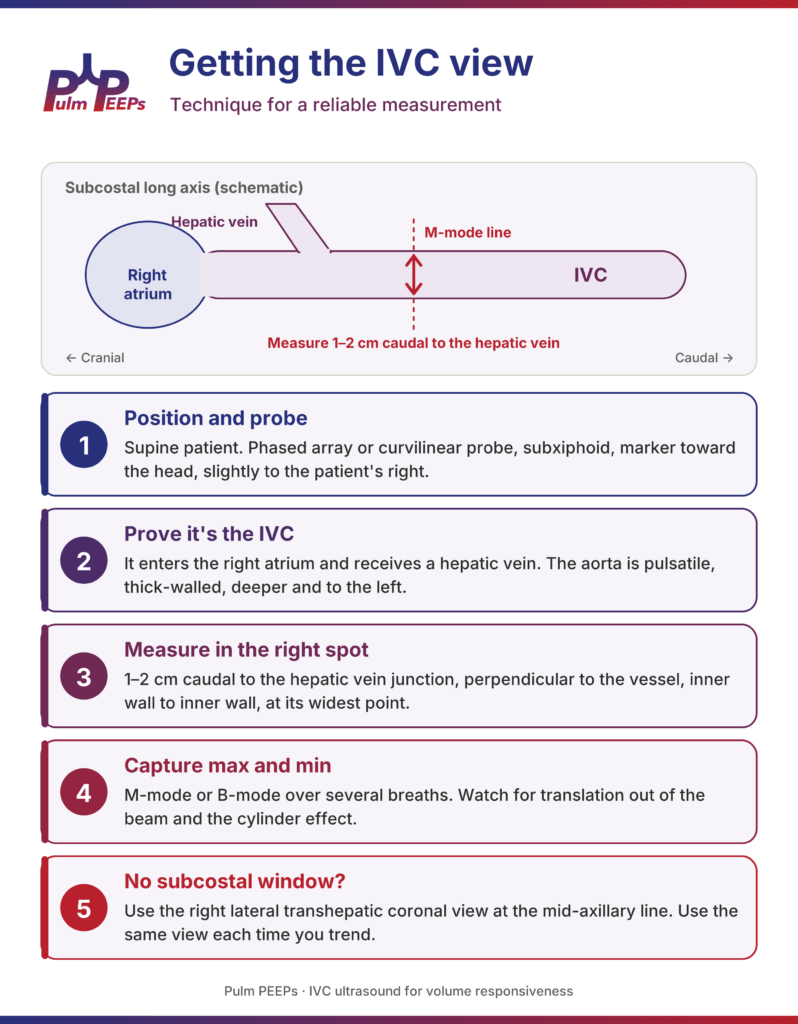
  • Find the IVC: start subxiphoid, slightly to the patient’s right, with the marker toward the head in a longitudinal (sagittal) plane. Many people start with a subcostal four-chamber view of the heart, then rotate to longitudinal to bring the IVC to the center of the screen. You want to see the IVC running through the liver into the right atrium.
  • Prove it’s the IVC: everyone has measured the aorta at some point. The IVC enters the right atrium and receives a hepatic vein. The aorta is thick-walled, pulsatile, deeper and to the patient’s left, and gives off the celiac and SMA rather than receiving hepatic veins. Fan over to find the aorta, or rotate to a transverse view to see both side by side. Color or pulsed-wave Doppler can help if you are unsure.
  • Measure in the right spot: 1 to 2 cm caudal to the hepatic vein junction (about 2 to 3 cm from the cavoatrial junction), perpendicular to the long axis of the vessel, inner wall to inner wall.
  • Capture the max and min: drop an M-mode line through that spot and record over several breaths. Many ultrasound machines have a built-in calculation package that will compute the index for you once you mark the maximum and minimum.
  • Watch for translation: the IVC moves with the diaphragm and can slide in and out of the M-mode line, which can look like collapse. Watch the B-mode clip, or measure in B-mode at a fixed anatomic landmark.
  • Avoid the cylinder effect: the IVC is a tube. A slice through its edge underestimates the diameter and can exaggerate collapse. Fan through the vessel and measure at its widest point.
  • No subcostal window? Post-op abdomen, body habitus and bowel gas are common in the ICU. Use the right lateral transhepatic coronal view at the mid-axillary line, using the liver as your window (the same view used in VExUS). Measurements are not perfectly interchangeable with the subcostal view, so use the same view each time you trend. If you cannot get confident landmarks, this may not be the right test for this patient.
Ivc 1 technique

The Intubated Patient: Distensibility

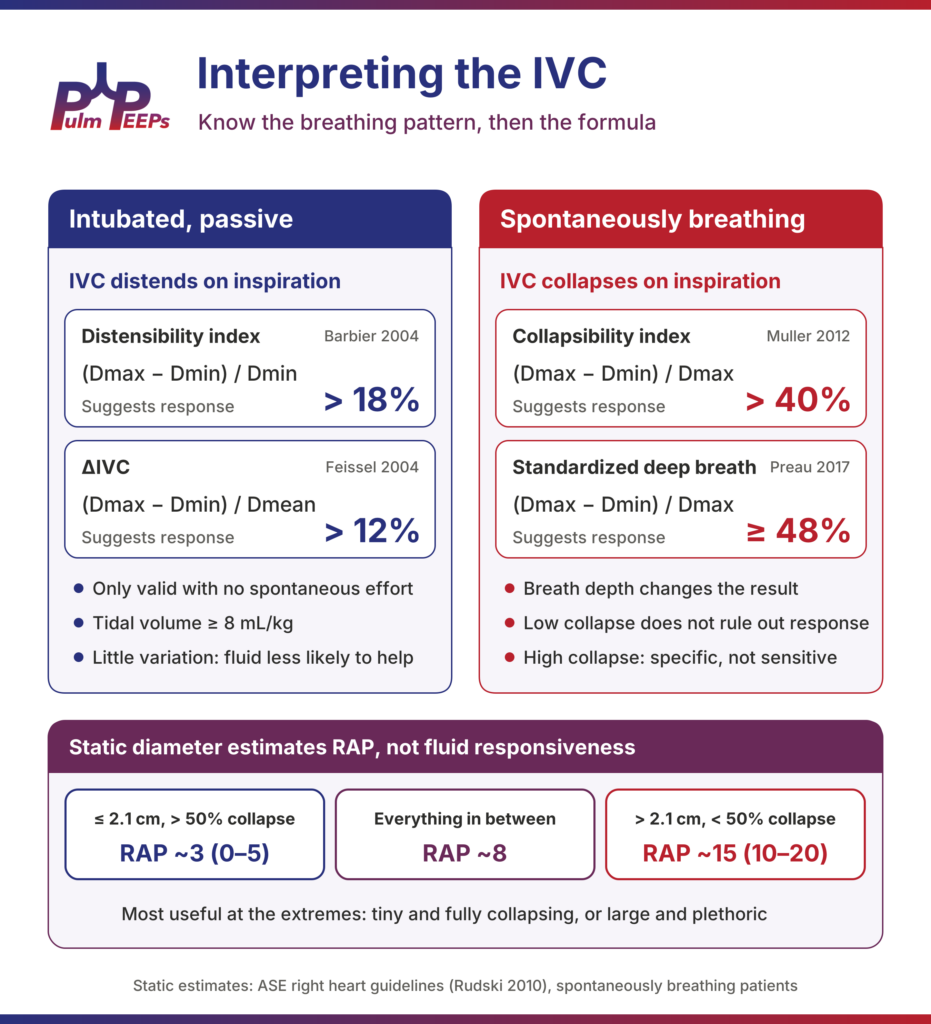
The IVC works best in mechanically ventilated patients because we control the breath. Two classic indices, both from 2004 and both in French septic shock patients, give us the numbers most people quote:

IndexFormulaCutoff suggesting responseStudy
Distensibility index (dIVC)(Dmax − Dmin) / Dmin> 18%Barbier 2004, n = 23: sensitivity and specificity ~90%
ΔIVC(Dmax − Dmin) / Dmean> 12%Feissel 2004, n = 39: PPV 93%, NPV 92%

Match the formula to the cutoff. Mixing them up is one of the most common errors. The easy way to remember it: 18 percent if you divide by the minimum, 12 percent if you divide by the mean. If your machine calculates the index, check which formula it uses.

Know the conditions these were validated in. Patients were fully passive on the ventilator, in volume control, with tidal volumes of about 8 to 10 mL/kg. In today’s ICU, with lung-protective ventilation at 6 mL/kg and patients often triggering breaths, those conditions frequently do not apply. Choose your patient carefully: passive on the vent, with an adequate tidal volume.

The Spontaneously Breathing Patient: Collapsibility

In the ED or on the floor, we are looking at collapsibility (the caval index): (Dmax − Dmin) / Dmax. Here the story gets messier. We do not control the rate or the effort, and a small shallow breath versus a big deep sniff gives very different collapsibility in the same patient at the same volume status. Many septic patients are also breathing hard, which changes intrathoracic dynamics considerably.

Three studies are worth knowing:

  • Muller 2012 (n = 40, acute circulatory failure): collapsibility > 40% had a sensitivity of 70% and specificity of 80%. A value below 40% did not rule out fluid responsiveness.
  • Airapetian 2015 (n = 59): overall performance was poor (AUC 0.62), but collapsibility > 42% was very specific (97%) with a sensitivity of only 31%.
  • Preau 2017 (n = 90, septic, non-intubated): standardizing the breath, a deep inspiration followed by passive exhalation, collapsibility ≥ 48% had a sensitivity of 84%, specificity of 90% and AUC of 0.89.

The practical takeaway: near-complete collapse, over 40 to 50 percent, especially with a standardized deep breath, makes fluid responsiveness more likely. A big number means something; a small number does not tell you much. And anyone can collapse their IVC if they are breathing hard enough, so in true respiratory distress this test is of little use.

What About Just the Size of the IVC?

“The IVC is flat, give fluid” is still heard on rounds, but the static diameter answers a different question. It comes from the echo world, where it is used to estimate right atrial pressure in spontaneously breathing patients, many of them outpatients. Per the American Society of Echocardiography right heart guidelines (Rudski 2010):

IVC diameter and sniff collapseEstimated RAP (mmHg)
≤ 2.1 cm and > 50% collapse~3 (0–5)
Everything in between~8
> 2.1 cm and < 50% collapse~15 (10–20)

Estimating right atrial pressure is not predicting fluid responsiveness. Decades of ICU data show that static pressures, even a directly measured CVP, are poor predictors of fluid responsiveness. This takes us right back to the difference between volume status and volume responsiveness.

The static IVC is most useful at the extremes. A tiny, nearly virtual IVC (under about 1 cm) in a hypotensive patient makes fluid responsiveness more likely. A large, non-collapsing IVC should make you pause and think about the right heart, tamponade or volume overload. As with our FeNO episode, the extremes are informative and the middle is gray.

Ivc 2 interpretation

What Do the Data Show?

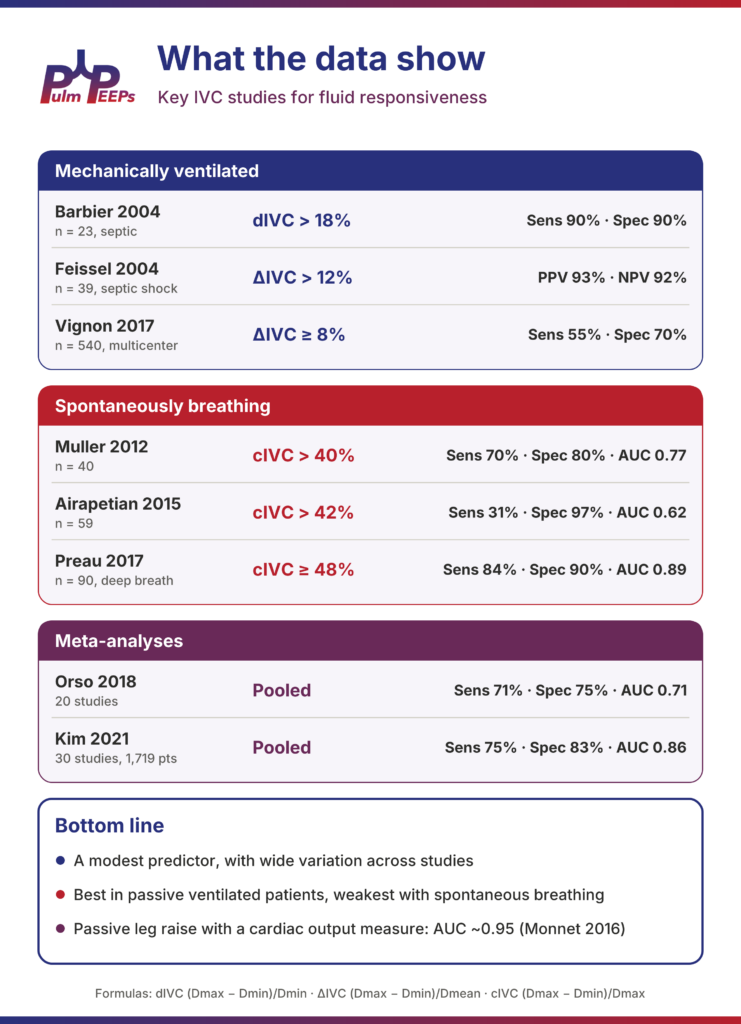
The IVC is a modest predictor of fluid responsiveness, with wide variation across studies. Performance is best in passive ventilated patients and weakest with spontaneous breathing:

StudyPopulationIndex and cutoffPerformance
Barbier 200423 ventilated, septicdIVC > 18%Sens 90%, spec 90%
Feissel 200439 ventilated, septic shockΔIVC > 12%PPV 93%, NPV 92%
Vignon 2017540 ventilated, multicenterΔIVC ≥ 8%Sens 55%, spec 70%
Muller 201240 spontaneously breathingcIVC > 40%Sens 70%, spec 80%, AUC 0.77
Airapetian 201559 spontaneously breathingcIVC > 42%Sens 31%, spec 97%, AUC 0.62
Preau 201790 spontaneously breathing, deep breathcIVC ≥ 48%Sens 84%, spec 90%, AUC 0.89
Orso (meta-analysis)20 studiesPooledSens 71%, spec 75%, AUC 0.71
Kim 2021 (meta-analysis)30 studies, 1,719 patientsPooledSens 75%, spec 83%, AUC 0.86

Note how much the large multicenter Vignon cohort pulls the ventilated numbers down compared with the small original studies. The meta-analyses are mixed and very heterogeneous: Orso and colleagues concluded the IVC is not a reliable predictor on its own, while Kim and colleagues found better pooled accuracy. Both pointed to huge variation in patient populations, formulas, cutoffs and how responsiveness was defined.

Putting it together: the IVC is fast, noninvasive and repeatable, and it is a useful piece of the puzzle. It should never be the only thing driving the decision to give fluid. When it really matters, a passive leg raise paired with a measure of cardiac output performs far better (pooled AUC ~0.95, Monnet 2016). We will cover LVOT VTI, pulse pressure variation and VExUS in future episodes.

Ivc 3 evidence

Pitfalls: When the IVC Can Mislead You

The patients we most want to answer this question for are often the ones in whom the IVC is least reliable.

On the ventilator

  • Spontaneous effort: patient-triggered breaths mix collapse and distension, and the cutoffs no longer apply.
  • Low tidal volume: at 6 mL/kg, the change in intrathoracic pressure may be too small to move the IVC, causing false negatives.
  • High PEEP: raises right atrial pressure on its own, distending the IVC and blunting variation.

In the patient

  • Raised intra-abdominal pressure: abdominal compartment syndrome, tense ascites, bowel distension or a recent abdominal surgery can compress the IVC, so a small, collapsible IVC may not mean responsive.
  • Right heart disease: RV failure, severe tricuspid regurgitation, pulmonary hypertension, PE and tamponade all give a plethoric IVC independent of volume. In tamponade or massive PE, of course, that plethoric IVC is important diagnostic information in its own right.
  • Vigorous breathing: in asthma, COPD exacerbations or any respiratory distress, forceful inspiration can collapse even a full IVC, and active exhalation distorts the measurement.

In the technique

  • Wrong vessel: the aorta is pulsatile, thick-walled and to the left. Confirm hepatic vein inflow.
  • Cylinder effect and translation: off-center slices and the IVC sliding out of the M-mode line both fake collapse.
  • Mismatched formula and cutoff: 18% goes with dividing by the minimum, 12% with dividing by the mean.

And remember: responsive does not mean needs fluid. Check tolerance too, with lung ultrasound and VExUS for venous congestion.

Ivc 4 pitfalls

The Five Pulm PEEPs Pearls

  1. Fluid responsive doesn’t mean fluid needed. Only about half of unstable ICU patients respond to fluid, and responsiveness is only one part of the decision. Always ask whether the patient needs, and can tolerate, more preload.
  2. Know the breathing pattern and the formula. Passive and intubated: distensibility over 18% (divide by the minimum) or over 12% (divide by the mean). Spontaneously breathing: collapsibility over 40 to 50% suggests response, especially with a standardized deep breath.
  3. The extremes are your friends. A tiny, fully collapsing IVC makes responsiveness more likely. A big, plethoric IVC should make you think about the right heart, tamponade or volume overload. A non-collapsing IVC in a spontaneously breathing patient doesn’t rule out response.
  4. Respect the pitfalls. Spontaneous effort on the vent, low tidal volumes, high PEEP, intra-abdominal hypertension and right heart disease all undermine the IVC, and they are common in our sickest patients. Prove it’s the IVC, and watch for the cylinder effect and translation.
  5. When it matters, go dynamic. A passive leg raise with LVOT VTI outperforms the IVC and works in many of the patients where the IVC fails.
Ivc 5 pearls

Scan carefully, interpret in context, and as always, keep breathing!

References and Further Reading

  • Michard F, Teboul JL. “Predicting fluid responsiveness in ICU patients: a critical analysis of the evidence.” Chest. 2002;121(6):2000–2008.
  • Barbier C, Loubières Y, Schmit C, et al. “Respiratory changes in inferior vena cava diameter are helpful in predicting fluid responsiveness in ventilated septic patients.” Intensive Care Med. 2004;30(9):1740–1746.
  • Feissel M, Michard F, Faller JP, Teboul JL. “The respiratory variation in inferior vena cava diameter as a guide to fluid therapy.” Intensive Care Med. 2004;30(9):1834–1837.
  • Muller L, Bobbia X, Toumi M, et al. “Respiratory variations of inferior vena cava diameter to predict fluid responsiveness in spontaneously breathing patients with acute circulatory failure: need for a cautious use.” Crit Care. 2012;16(5):R188.
  • Airapetian N, Maizel J, Alyamani O, et al. “Does inferior vena cava respiratory variability predict fluid responsiveness in spontaneously breathing patients?” Crit Care. 2015;19:400.
  • Preau S, Bortolotti P, Colling D, et al. “Diagnostic accuracy of the inferior vena cava collapsibility to predict fluid responsiveness in spontaneously breathing patients with sepsis and acute circulatory failure.” Crit Care Med. 2017;45(3):e290–e297.
  • Vignon P, Repessé X, Bégot E, et al. “Comparison of echocardiographic indices used to predict fluid responsiveness in ventilated patients.” Am J Respir Crit Care Med. 2017;195(8):1022–1032.
  • Orso D, Paoli I, Piani T, et al. “Accuracy of ultrasonographic measurements of inferior vena cava to determine fluid responsiveness: a systematic review and meta-analysis.” J Intensive Care Med. 2020;35(4):354–363.
  • Kim DW, Chung S, Kang WS, Kim J. “Diagnostic accuracy of ultrasonographic respiratory variation in the inferior vena cava, subclavian vein, internal jugular vein, and femoral vein diameter to predict fluid responsiveness: a systematic review and meta-analysis.” Diagnostics (Basel). 2021;12(1):49.
  • Rudski LG, Lai WW, Afilalo J, et al. “Guidelines for the echocardiographic assessment of the right heart in adults.” J Am Soc Echocardiogr. 2010;23(7):685–713.
  • Monnet X, Marik P, Teboul JL. “Passive leg raising for predicting fluid responsiveness: a systematic review and meta-analysis.” Intensive Care Med. 2016;42(12):1935–1947.

124. Fractional Exhaled Nitric Oxide (FeNO)

PPP Cover Images

Furf and Monty are back! For our first episode back in the studio, we’re returning with a Pulm PEEPs Pearls episode on a test that is showing up more and more in pulmonary clinic: fractional exhaled nitric oxide, or FeNO. Using a patient with asthma-like symptoms and a FeNO that lands right in the middle, Furf and Monty walk through what the test measures, how to interpret the number, what can push it up or down, and how to use it for both diagnosis and monitoring.

Contributors

This episode was prepared with research by Pulm PEEPs Associate Editor George Doumat.

Key Learning Points

The Case

A 28-year-old accountant presents with six months of episodic cough and wheeze. Her spirometry is normal with no bronchodilator response, but her FeNO comes back at 42 ppb. Does she have asthma?

The honest answer: maybe. FeNO is not a yes/no asthma test, and a single number has to be interpreted in clinical context.

What Is FeNO Measuring?

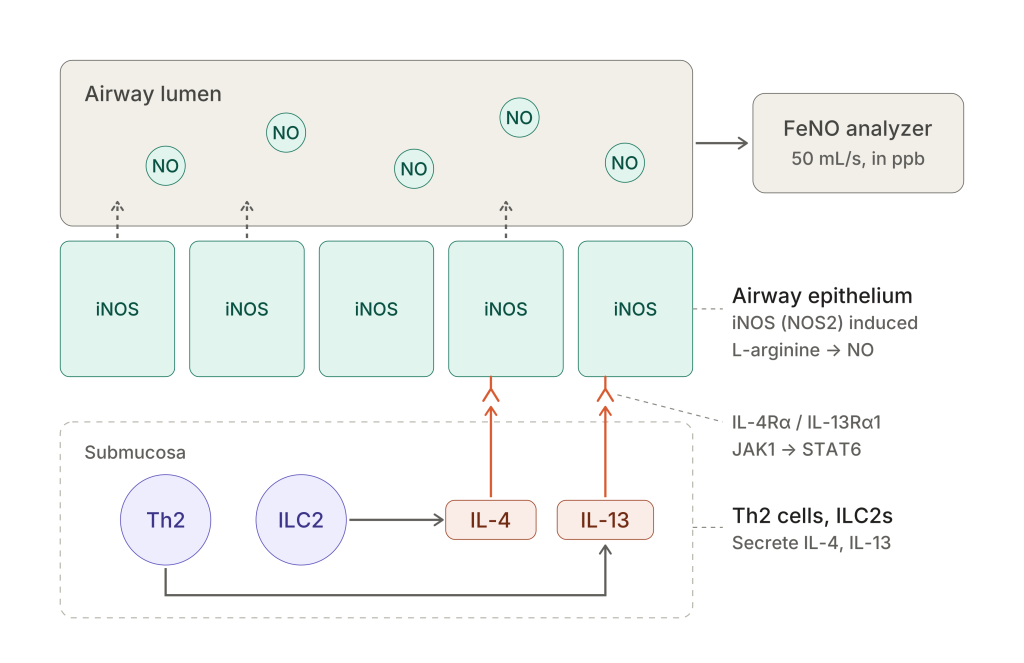
FeNO measures the concentration of nitric oxide in exhaled breath. In type 2 airway inflammation, Th2 cells and ILC2s release IL-4 and IL-13, which signal through the IL-4Rα/IL-13Rα1 receptor (JAK1 → STAT6) to induce iNOS (NOS2) in airway epithelial cells. iNOS converts L-arginine to nitric oxide, which diffuses into the airway lumen and is measured by the analyzer at a standardized exhalation flow of 50 mL/s, reported in parts per billion (ppb).

Bottom line: FeNO gives us a window into type 2 (eosinophilic, allergic-pathway) airway inflammation at the cellular level, something spirometry can’t tell us.

Feno diagram

Three Tests, Three Questions

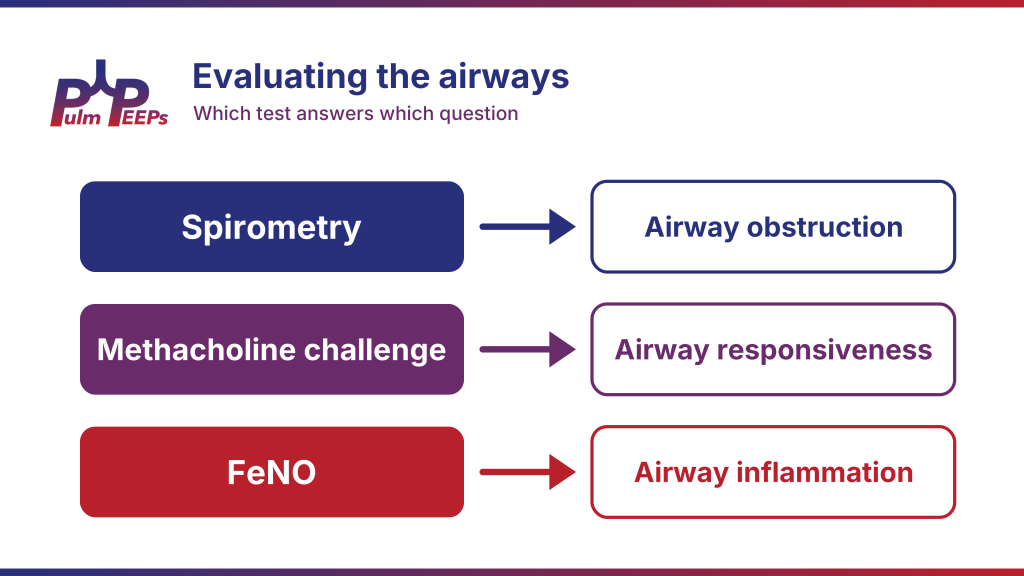
Each airway test answers a different question, and all three can feed into an asthma diagnosis:

TestQuestion It Answers
SpirometryIs there airflow obstruction?
Methacholine challengeIs there airway hyperresponsiveness?
FeNOIs there type 2 airway inflammation?

These tests don’t always point in the same direction. A patient can have normal spirometry and a negative methacholine challenge but still have an elevated FeNO if there is active eosinophilic inflammation, and the reverse can happen too.

Airway tests

Interpreting the Number

Feno interpretation vertical

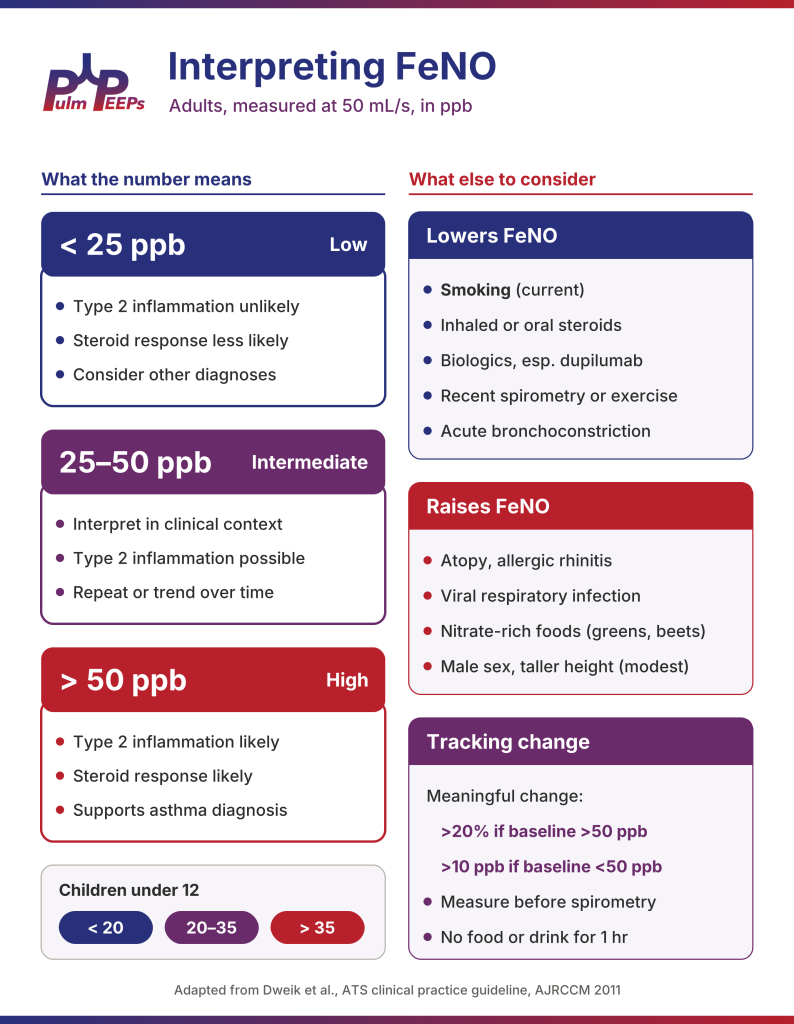
The ATS thresholds for adults are easy to remember because they move in 25s:

FeNO (adults)CategoryWhat It Suggests
< 25 ppbLowType 2 inflammation unlikely; steroid response less likely; consider other diagnoses
25–50 ppbIntermediateType 2 inflammation possible; interpret in clinical context; repeat or trend over time
> 50 ppbHighType 2 inflammation likely; steroid response likely; supports an asthma diagnosis in the right context

The extremes are your friends. A value below 25 ppb or above 50 ppb is far more actionable than one in the intermediate range. In the 25–50 zone, we have to do some doctoring.

Children are different: in children under 12, cutoffs are < 20 ppb (low), 20–35 ppb (intermediate), and > 35 ppb (high). Don’t carry adult thresholds over.

What Moves the Number

Before interpreting a value, think about what might be confounding it.

Lowers FeNO:

  • Current smoking. A “normal” value in a smoker can be falsely reassuring.
  • Inhaled or oral corticosteroids, which suppress the type 2 signal.
  • Biologics, especially dupilumab (which blocks IL-4Rα).
  • Recent spirometry or exercise.
  • Acute bronchoconstriction. A patient in a severe flare can’t exhale fully, so the value may be artificially low. This is not a test for the middle of an exacerbation.

Raises FeNO:

  • Atopy and allergic rhinitis, or ongoing allergen exposure
  • Viral respiratory infection
  • Nitrate-rich foods (leafy greens, beets)
  • Male sex and taller height (modest effect)

Testing tips: measure FeNO before spirometry, and have patients avoid food and drink for 1 hour beforehand.

Back to Our Patient

Our patient’s FeNO of 42 ppb is intermediate. It isn’t a diagnosis, but this is exactly the scenario where FeNO earns its keep: she has asthma-like symptoms and the usual physiologic testing hasn’t given us an answer. An elevated value adds evidence that a type 2 eosinophilic process may be present in her airways.

Two important caveats:

  • A positive FeNO supports the phenotype, but doesn’t close the case. Current asthma guidelines incorporate FeNO into diagnosis and monitoring, but it belongs inside the diagnostic pathway as one more piece of evidence. Patients are sometimes labeled with asthma based on a single intermediate FeNO, only to have a normal methacholine challenge and an entirely different explanation for their symptoms.
  • A low FeNO doesn’t rule out asthma. Non-eosinophilic and neutrophilic asthma phenotypes exist, and FeNO isn’t designed to detect them.

Using FeNO to Monitor Asthma

Once a patient carries an asthma diagnosis, FeNO can become actionable.

Persistent symptoms + persistently high FeNO: There is still a type 2 inflammatory signal, but don’t reflexively escalate inhaled corticosteroids. First ask why the signal is still there:

  • Is the patient actually taking the ICS (adherence)?
  • Are they using the inhaler correctly (technique and delivery)?
  • Is there ongoing allergen exposure?
  • Is the current anti-inflammatory dose simply inadequate?

Sometimes a high FeNO is telling you about adherence or delivery, not that the prescription isn’t strong enough.

Persistent symptoms + low FeNO: Especially if blood eosinophils are also low, pause before adding more ICS. Consider a different asthma phenotype, an alternative diagnosis, or another contributor to the symptoms. FeNO can keep us from treating every symptom as though it means more steroid.

The evidence: A 2023 systematic review and meta-analysis of 12 RCTs in adults found that FeNO-guided treatment probably reduces exacerbations compared with symptom-guided treatment, with less clear effects on quality of life, lung function, and other outcomes.

Follow the trend, not the cutoff. Once you’re following a patient over time, they become their own control, and the trajectory matters more than whether a value crosses from 48 to 52 ppb. A meaningful change is generally considered:

  • > 20% if the baseline is > 50 ppb
  • > 10 ppb if the baseline is < 50 ppb

An elevated FeNO that falls meaningfully after starting ICS supports that you’ve actually changed the airway inflammation.

Beyond Asthma: Chronic Cough

FeNO can also help in the workup of chronic cough. A patient with chronic cough, an elevated FeNO, normal spirometry, and a negative methacholine challenge may have non-asthmatic eosinophilic bronchitis, which can respond to inhaled corticosteroids. Systematically working through and crossing off treatable causes is also what allows us to confidently name refractory chronic cough. For more, check out our episode Pulm PEEPs & Irish Thoracic Society: Understanding Refractory Chronic Cough.

The Four Pulm PEEPs Pearls

Feno pearls
  1. Inflammation, not obstruction: FeNO measures type 2 eosinophilic airway inflammation, not airflow obstruction. That’s why it complements spirometry and methacholine challenge rather than replacing either one.
  2. The extremes are your friends: Above 50 ppb supports type 2 inflammation and makes steroid responsiveness more likely in the right clinical context. Below 25 ppb argues against active eosinophilic disease. From 25 to 50 ppb, context matters.
  3. Supports, but doesn’t diagnose: FeNO can support an asthma diagnosis, but it doesn’t make the diagnosis by itself, and a low FeNO does not rule out asthma.
  4. Persistently high? Ask why: Before simply escalating therapy, check adherence, inhaler technique, allergen exposure, and whether anti-inflammatory treatment is adequate. When following someone over time, the trend may be more informative than any single number.

Remember: we’re treating the patient, not the FeNO number.

References and Further Reading

Dweik, Raed A et al. “An official ATS clinical practice guideline: interpretation of exhaled nitric oxide levels (FENO) for clinical applications.” American journal of respiratory and critical care medicine vol. 184,5 (2011): 602-15. doi:10.1164/rccm.9120-11ST

American Thoracic Society; European Respiratory Society. “ATS/ERS recommendations for standardized procedures for the online and offline measurement of exhaled lower respiratory nitric oxide and nasal nitric oxide, 2005.” American journal of respiratory and critical care medicine vol. 171,8 (2005): 912-30. doi:10.1164/rccm.200406-710ST

Korevaar, Daniël A et al. “Effectiveness of FeNO-guided treatment in adult asthma patients: A systematic review and meta-analysis.” Clinical and experimental allergy vol. 53,8 (2023): 798-808. doi:10.1111/cea.14359

Petsky, Helen L et al. “Exhaled nitric oxide levels to guide treatment for adults with asthma.” The Cochrane database of systematic reviews vol. 9,9 CD011440. 1 Sep. 2016, doi:10.1002/14651858.CD011440.pub2

Louis, Renaud et al. “European Respiratory Society guidelines for the diagnosis of asthma in adults.” The European respiratory journal vol. 60,3 2101585. 15 Sep. 2022, doi:10.1183/13993003.01585-2021

Expert Panel Working Group of the National Heart, Lung, and Blood Institute (NHLBI). “2020 Focused Updates to the Asthma Management Guidelines: A Report from the National Asthma Education and Prevention Program Coordinating Committee Expert Panel Working Group.” The Journal of allergy and clinical immunology vol. 146,6 (2020): 1217-1270. doi:10.1016/j.jaci.2020.10.003

Global Initiative for Asthma. Global Strategy for Asthma Management and Prevention. Updated annually. Available at ginasthma.org.

123. Critical Care Medicine for Non-Intensivists

PPP Cover Images (1)

Today we’re joined by Dr. Molly Hayes and talking about an upcoming CME course: Principles of Critical Care Medicine for Non-Intensive Care Specialists. This is a wonderful education course covering a wide array of topics in critical care in a case-based, systematic, and peer-reviewed fashion. The course is interactive and all resources will be available for attendees afterwards for their review. You can sign up at https://learn.hms.harvard.edu/criticalmed and save using the discount code “PulmPEEPS50”!

Dr. Molly Hayes is an Associate Professor of Medicine at Beth Israel Deaconess Medical Center and Harvard Medical School, the Director of the MICU at BIDMC, and the Director of External Education at the Carl J Shapiro Institute for Education and Research. She additionally is a co-founder of the BIDMC Center for Humanizing the ICU.

https://learn.hms.harvard.edu/criticalmed

https://www.pulmpeeps.com/2025/08/12/106-pulm-peeps-p…-ici-pneumonitis

Managing Immune Checkpoint Inhibitor Pneumonitis in the ICU. Montemayor, Kristina et al.CHEST Critical Care, Volume 3, Issue 1, 100126

122. Pulm PEEPs Pearls: Steroids in Sepsis

PPP Cover Images (1)

Today we have another Pulm PEEPs Pearls episode about a core critical care topic. Furf and Monty will be giving a high level overview of the use of steroids in sepsis including a review of the relevant literature and recent guidelines, and pragmatic bedside points.

This episode was prepared with research by Pulm PEEPs Associate Editor George Doumat.

Dustin Latimer, another Pulm PEEPs Associate Editor, assisted with audio and video editing.

Why Steroids in Sepsis?

Steroids do not treat the infection — antimicrobials are always first and remain the cornerstone. The goal is addressing critical illness–related corticosteroid insufficiency (CIRCI), where cortisol production cannot keep up with the overwhelming inflammatory demand of septic shock.

Hydrocortisone helps in two main ways:

  • Blunts the dysregulated inflammatory response — tempers the excessive vasodilation and febrile response that drive harm beyond the infection itself.
  • Restores vascular sensitivity to catecholamines — sepsis downregulates adrenergic receptors; steroids turn that responsiveness back on.

Clinical takeaway: The first thing you notice is vasopressor weaning (or a bend in the escalation curve) — not a rapid improvement in fever or white count.

Caveat: These trials predate modern sepsis phenotyping. None distinguish hyperinflammatory vs. hypoinflammatory responders — they treat all comers.

The Evidence: Four Landmark Trials

Every IM resident and critical care fellow will eventually journal-club these four. The most consistent signal across all of them is faster shock reversal and reduced vasopressor use; the mortality question remains unsettled.

Trial (Year)NRegimenKey Finding
Annane (2002)~300Hydrocortisone + fludrocortisoneMortality benefit in ACTH non-responders; criticized methodology and messy cortisol-response testing; not cleanly replicated.
CORTICUS (2008)~500Hydrocortisone aloneFaster shock reversal but no mortality benefit, regardless of cortisol responsiveness. Raised (later allayed) superinfection concern. Cornerstone for abandoning routine cort-stim testing.
ADRENAL (2018)~3,800Hydrocortisone aloneFaster vasopressor weaning; no 90-day mortality benefit.
APROCCHSS (2018)~1,200Hydrocortisone + fludrocortisoneMortality benefit at 90 days.

Bottom line: Faster shock reversal is consistent. Mortality benefit appears in 2 of 4 trials (both used fludrocortisone) but not the others. A 2026 meta-analysis showed benefit for hydrocortisone + fludrocortisone vs. placebo, but

not for hydrocortisone + fludrocortisone vs. hydrocortisone alone — suggesting hydrocortisone drives the main effect.

Who Gets Steroids, and When?

  • 2021 Surviving Sepsis: Consider steroids for norepinephrine or epinephrine ≥ 0.25 mcg/kg/min for ≥ 4 hours despite adequate resuscitation — a reasonable bedside trigger.
  • Early 2026 update: Moved away from a specific numeric trigger — consider steroids when a septic patient is not responding well to vasopressors or has escalating requirements. Make a clinical decision. (Quality of evidence: low to moderate.)
  • Go faster than the threshold when: Known/suspected adrenal insufficiency or home steroids, or florid pressor-requiring shock on arrival.

A practical escalation sequence: escalating norepinephrine → add vasopressin (per VASST) → then add steroids if requirements keep climbing.

Do NOT wait for an ACTH stimulation test. It does not reliably predict who responds and only delays treatment. Sepsis is an elevated-cortisol state but can dissociate ACTH and cortisol, and cortisol-binding globulin is depleted — the test is too messy to guide care.

What to Give: The Regimen

  • Standard dose: Hydrocortisone 200 mg/day, typically 50 mg IV Q6H. (Original trials often used continuous infusions, rarely used in the U.S.) Some start with a 100 mg bolus to gain control.
  • Higher dose: If chronically on steroids / adrenally insufficient, consider ~300 mg/day (e.g., 100 mg Q8H).
  • Fludrocortisone: Unsettled. The two mortality-benefit trials added it (50 mcg PO/NG/OG daily), but hydrocortisone already has mineralocorticoid activity and meta-analyses don’t show added benefit over hydrocortisone alone. Most clinicians omit it — adding it is reasonable and safe, just be honest about the uncertainty.

Duration & Tapering

  • Typical course: ~7 days is most common. Trial practices varied (ADRENAL ~7 days; VANISH used a taper after 6 days; some continue until pressors are off).
  • No taper needed. You do not need to taper for adrenal insufficiency after a short course — just stop. If pressors dramatically rebound, you can restart, but most patients have gained the benefit they’ll get by day 7.

Pitfalls & Safety

  • Hyperglycemia: Expected and must be managed (monitor closely; insulin drip if needed). No signal for major DKA / severe complications in the trials.
  • Superinfection / fungal infection: The most-quoted concern, but the overall literature does not show a convincing, statistically significant increase. Be disciplined about stopping on schedule.
  • Muscle weakness: Steroids can worsen critical illness myopathy; a short 7-day course likely has limited effect, but be aware.
  • Other: GI bleeding (follow general PPI prophylaxis guidance) and sodium disturbances (watch for hyper-/hyponatremia).

Two things we know: (1) steroids shorten duration of vasopressor support, and (2) they are relatively safe in sepsis. Whether they improve mortality — and in whom — remains open.

The Five Pulm PEEPs Pearls

  1. Mechanism: Steroids restore catecholamine vascular sensitivity and blunt dysregulated inflammation. The clinical target is vasopressor weaning, not infection treatment.
  2. Evidence: Faster shock reversal is the most consistent finding. Mortality benefit is seen in 2 of 4 trials but not the others — still controversial. Some patients likely benefit; we don’t yet know who.
  3. Trigger: A practical 2021 threshold is levo/epi ≥ 0.25 mcg/kg/min for ≥ 4 hours. Newer guidance drops the strict number — make a clinical decision based on poor pressor response or escalation.
  4. Dose: Hydrocortisone 200 mg/day (e.g., 50 mg Q6H). Adding fludrocortisone mirrors two trials, but meta-analyses find no benefit over hydrocortisone alone.
  5. Safety: Steroids appear safe in sepsis. Monitor and treat hyperglycemia; no marked increase in superinfection.

Annane, Djillali et al. “Effect of treatment with low doses of hydrocortisone and fludrocortisone on mortality in patients with septic shock.” JAMA vol. 288,7 (2002): 862-71. doi:10.1001/jama.288.7.862

Sprung, Charles L et al. “Hydrocortisone therapy for patients with septic shock.” The New England journal of medicine vol. 358,2 (2008): 111-24. doi:10.1056/NEJMoa071366

Venkatesh, Balasubramanian et al. “Adjunctive Glucocorticoid Therapy in Patients with Septic Shock.” The New England journal of medicine vol. 378,9 (2018): 797-808. doi:10.1056/NEJMoa1705835

Annane, Djillali et al. “Hydrocortisone plus Fludrocortisone for Adults with Septic Shock.” The New England journal of medicine vol. 378,9 (2018): 809-818. doi:10.1056/NEJMoa1705716

Sun, Alin et al. “Correction: Hydrocortisone combined with fludrocortisone for treatment of adults with septic shock: an updated meta-analysis and systematic review.” Frontiers in medicine vol. 13 1811616. 2 Mar. 2026, doi:10.3389/fmed.2026.1811616

Prescott, Hallie C et al. “Executive Summary: Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2026.” Critical care medicine vol. 54,4 (2026): 715-724. doi:10.1097/CCM.0000000000007089

121. My Diagnosis

PPP Cover Images (2)

Hey everyone, Dave Furfaro here from Pulm PEEPs. As you may have noticed in the last few weeks and months, we’ve had a little bit of a decrease in the content that we’ve been putting out, and I just wanted to share a couple things with you about why that is and the future of Pulm PEEPs coming up. In December of 2025, I was diagnosed with a large myxoid liposarcoma in my leg, and since then, I have been undergoing treatment for that.

Overall, treatment has been going well, but it’s certainly been a long road that, continues, and I hope that it continues to trend positively. Kristina has been an unbelievable support during this. We have continued to work on some content as a great way and distraction for me at times, but we haven’t been able to keep up the same pace of content that we usually put out. And given everything that is going on, I actually anticipate that will continue for a few months. Ee haven’t said anything so far yet because we were still figuring it out ourselves, but now we just wanted you all to know that, we, love doing Pulm PEEPs. We’re very committed to it. We wanna get back to doing it as consistently as we have been previously, and we plan on doing that, but it likely will be a little bit of time, and this is why.

I also may be sharing more about my journey through the medical system as a patient, in the future, but for now, I’m really just focusing on my treatment, my health, and my family. So the summer months will likely be, much slower, maybe even a break off together, and look forward to recovering and getting back to producing more regular Pulm PEEPs content in the Fall.

Hope everybody who’s listening is doing well. Thank you all, as always, for being supportive, for listening to the podcast, for reaching out to us on social media, for saying hi to us in person at conferences. It’s been, a true delight, and we can’t wait to get back to business as usual. Okay, everybody. Take good care of patients, be safe, be well, and we’ll see you soon.

120. Pulm PEEPs & Irish Thoracic Society: Understanding Refractory Chronic Cough

PPP Cover Images (3)

We’re excited today to launch our first episode in collaboration with the Irish Thoracic Society and their podcast series. The Irish Thoracic Society represents respiratory professionals throughout Ireland and is dedicated to championing excellence in the prevention, diagnosis, and clinical care of respiratory disease through its work in advocacy, education and research.

In today’s episode, we explore the complex and often overlooked world of refractory chronic cough — a condition that can significantly impact patients’ quality of life but is frequently misunderstood or underdiagnosed. With insights from leading respiratory specialists in Ireland and the United States, we discuss the latest thinking on diagnosis, management, and emerging treatments aimed at improving outcomes for patients and helping clinicians navigate this challenging area of respiratory medicine.

Joining us are renowned experts Professor Lorcan McGarvey and Professor Brendan Canning, both internationally recognised leaders in respiratory medicine and cough research. Together, they share their perspectives on the neurobiology of chronic cough, the considerable morbidity experienced by patients, and how clinicians can approach diagnostic investigations more effectively.

We also explore current treatment strategies and promising new therapies on the horizon as chronic cough increasingly gains recognition as a disease in its own right — rather than simply a symptom. Whether you’re a clinician, researcher, or simply interested in advances in respiratory medicine, this episode offers valuable insights into a condition that is finally receiving the attention it deserves.

The definitions and classifications of chronic cough, including unexplained, refractory, and unexplained refractory cough

The importance of a thorough clinical history and focused diagnostics over exhaustive testing

Common causes of chronic cough

The role of personalized, multidisciplinary management—combining pharmacologic, speech therapy, and psychological support—to improve quality of life for even the most challenging patients.

The concept of cough hypersensitivity syndrome and its role in refractory cases

Evidence-based approach to treatment, including pharmacologic and non-pharmacologic options

Emerging therapies on the horizon, including novel receptor modulators and neuromodulatory agents and ongoing clinical trials in this rapidly evolving field

The impact of chronic cough on mental health, social life, and overall quality of life

The importance of reframing chronic cough as a disease entity in its own right

Chung KF, Pavord ID. Prevalence, pathogenesis, and causes of chronic cough. Lancet. 2008;371(9621):1364-1374.

Gibson PG, Vertigan AE. Management of chronic refractory cough. BMJ. 2015;351:h5590.

Matsumoto H, Kanemitsu Y, Ohe M, Tanaka H, Terada K, Nishi K, et al. Real-world usage and response to gefapixant in refractory chronic cough. ERJ Open Res. 2025;11(4):01037-2024. doi:10.1183/23120541.01037-2024.

McGarvey LP, Birring SS. Cough hypersensitivity syndrome: a novel paradigm for understanding cough. Lancet Respir Med. 2014;2(8):647-656.

Morice AH, Millqvist E, Bieksiene K, Birring SS, Dicpinigaitis P, Ribas CD, et al. ERS guidelines on the diagnosis and treatment of chronic cough in adults and children. Eur Respir J. 2020;55(1):1901136.

Parker SM, Smith JA, Birring SS, Chamberlain-Mitchell S, Gruffydd-Jones K, Haines J, et al. British Thoracic Society clinical statement on chronic cough in adults. Thorax. 2023;78(Suppl 1):S3-S19.

Smith JA, Woodcock A. Chronic cough. N Engl J Med. 2006;354(2):136-144.

Song WJ, Dupont L, Birring SS, Chung KF, Dąbrowska M, Dicpinigaitis P, et al. Consensus goals and standards for specialist cough clinics: the NEUROCOUGH international Delphi study. ERJ Open Res. 2023;9(6):00618-2023. doi:10.1183/23120541.00618-2023.

Song WJ, McGarvey L, Cho PSP, Mazzone SB, Chung KF, editors. Chronic cough. Sheffield: European Respiratory Society; 2025.

119. Guideline Series: Pulmonary Embolism

PPP Cover Images (4)

We are unbelievably excited this week to be reviewing the hot-off-the-presses 2026 Multi-Society (AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN) Pulmonary Embolism Guidelines with lead author Dr. Mark A. Creager. We will talk about key updates in these guidelines compared to prior practice, including the new risk classification model, and provide an overview from diagnosis to follow-up. Given the clinical importance and prevalence of pulmonary embolism, these guidelines are certainly going to shape practice going forward, so this episode is a can’t miss!

Watch the full video of this episode with graphics and helpful teaching visuals on our YouTube channel: https://www.youtube.com/@pulmpeeps

Dr. Mark Creager is a Professor of Medicine at Dartmouth Hitchcock Medical Center where he specializes in Cardiovascular Medicine with an emphasis on venous thromboembolic disease. He served as the lead author of the 2026 Pulmonary Embolism Guidelines.

Creager MA, Barnes GD, Giri J, Mukherjee D, Jones WS, Burnett AE, Carman T, Casanegra AI, Castellucci LA, Clark SM, Cushman M, de Wit K, Eaves JM, Fang MC, Goldberg JB, Henkin S, Johnston-Cox H, Kadavath S, Kadian-Dodov D, Keeling WB, Klein AJP, Li J, McDaniel MC, Moores LK, Piazza G, Prenger KS, Pugliese SC, Ranade M, Rosovsky RP, Russo F, Secemsky EA, Sista AK, Tefera L, Weinberg I, Westafer LM, Young MN. 2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN Guideline for the Evaluation and Management of Acute Pulmonary Embolism in Adults: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. J Am Coll Cardiol. 2026 Feb 19:S0735-1097(25)10161-7. doi: 10.1016/j.jacc.2025.11.005. Epub ahead of print. PMID: 41712898.

Why these guidelines matter:

This is the first joint AHA/ACC clinical practice guideline specifically on acute PE, bringing together a truly multidisciplinary writing committee (cardiology, pulmonology, hematology, emergency medicine, interventional radiology, surgery, and others). Prior guidelines existed from individual societies, but nothing this comprehensive had been updated in roughly five to six years.

New PE clinical categories (A through E):

One of the most impactful changes is replacing the old “massive/submassive” and “low/intermediate/high risk” labels with five categories that form a severity continuum. Category A is subclinical (incidental PE found on imaging in asymptomatic patients). Category B covers symptomatic but low-severity patients. Category C is where much of the clinical complexity lives — symptomatic, hemodynamically stable patients subdivided into C1, C2, and C3 based on RV function and biomarkers. Category D represents incipient cardiopulmonary failure (transient hypotension, normotensive shock with end-organ dysfunction). Category E is frank cardiopulmonary failure, with E2 being the sickest — refractory or recurrent cardiac arrest. Respiratory modifiers (hypoxia requiring supplemental oxygen) layer onto C, D, and E.

Diagnostic approach:

Clinical evaluation comes first — history, exam, and validated decision tools (Wells score, revised Geneva, PERC). If clinical probability is low and D-dimer is normal, imaging can be safely avoided. If either is concerning, imaging is warranted. CTPA remains the preferred imaging modality due to superior sensitivity, specificity, wide availability, and ability to assess clot burden and alternative diagnoses. VQ scanning is still appropriate when CTPA is contraindicated, and VQ SPECT offers better reproducibility and specificity than traditional planar VQ if available. Echocardiography is not a diagnostic test for PE but is important for risk stratification — RV size, TAPSE, and tissue Doppler measures all contribute prognostic information.

Anticoagulation updates:

Anticoagulation remains the cornerstone of treatment. For patients potentially needing advanced therapies (C3, D, E), parenteral anticoagulation is started first. A notable recommendation: low molecular weight heparin is generally preferred over unfractionated heparin, based on evidence showing more effective VTE risk reduction, more predictable pharmacokinetics, no need for routine monitoring, lower rates of heparin-induced thrombocytopenia, and no increase in major bleeding. The committee acknowledged this may create discomfort for clinicians accustomed to unfractionated heparin’s easy reversibility, but the difficulty of achieving and maintaining therapeutic levels with UFH was a significant concern.

Advanced therapies:

Catheter-based thrombolysis, mechanical thrombectomy, systemic thrombolysis, and surgical embolectomy all received mostly class 2B recommendations (“can consider”) for C3 and D categories, reflecting that current evidence shows improvement in short-term surrogate measures (RV/LV ratio, hemodynamics) but lacks definitive hard outcome data on mortality. For category E1 patients, recommendations are stronger (class 2A). Multiple trials are expected soon — HI-PEITHO, PEERLESS-2, PE-TRACT, PERSEVERE, TORPEDO, and PROG — that should substantially inform future updates.

PERT teams:

Pulmonary embolism response teams are encouraged, particularly for C3, D, and E patients. They’ve been shown to reduce length of stay. For institutions without PERT capability, establishing consultation networks with larger centers is recommended.

Post-PE follow-up:

Patients shouldn’t be “left in the wilderness” after discharge. The guidelines recommend communication within the first week to ensure understanding of diagnosis and treatment, an in-person visit at or before three months to assess for persistent symptoms and discuss anticoagulation duration, ongoing surveillance for chronic thromboembolic pulmonary disease, and periodic reassessment for those on extended anticoagulation.

Infographics

118. Pulm PEEPs Pearls: Methacholine Challenge

PPP Cover Images

Furf and Monty are back with another Pulm PEEPs Pearls episode. The topic of today’s discussion is an often discussed, but often misunderstood, test; the methacholine challenge. They’ll review when to utilize this test, how it should be performed, and the appropriate interpretation.

This episode was prepared with research by Pulm PEEPs Associate Editor George Doumat.

Dustin Latimer, another Pulm PEEPs Associate Editor, assisted with audio and video editing.

What the Test Measures

  • Methacholine challenge is a direct bronchial provocation test of airway hyperresponsiveness (AHR), a core physiologic feature of asthma.
  • Anyone will bronchoconstrict at high enough concentrations — the test looks for an abnormal threshold.
  • The key endpoint is the PC20: the methacholine concentration causing a 20% fall in FEV1.
    • Abnormal in adults: PC20 ≤ 8–16 mg/mL

Test Performance

  • Meta-analyses: pooled sensitivity ~60%, specificity ~90%.
  • Real-world cohorts: sensitivity 55–62%, specificity 56–100% (varies by population, protocol, and threshold used).
  • Not a standalone yes/no test — best used as part of a broader diagnostic pathway.

Where It Fits in the Asthma Workup

The test belongs in a stepwise approach:

  1. Step 1: Spirometry + bronchodilator response
  2. Step 2: Add FeNO and/or peak flow variability (if available)
  3. Step 3: If the picture is still unclear → methacholine challenge

It is most useful for symptomatic patients with normal spirometry and no bronchodilator reversibility. Given its cost, mild risk, and discomfort, it should not be a first-line test — most asthma diagnoses do not require it.

Technique and Medication Prep

Technique

  • ERS guidelines favor tidal breathing over deep inspiratory maneuvers.
  • Deep breaths can be bronchoprotective and blunt the response, reducing sensitivity — especially in mild or well-controlled asthma.

Medication Washout (to Avoid False Negatives)

Medication ClassWashout Period
Short-acting beta-agonists (SABA)≥ 6 hours
Long-acting beta-agonists (LABA)~24 hours
Ultra-long-acting beta-agonists~48 hours
Short-acting anticholinergics (e.g., ipratropium)~12 hours
Long-acting muscarinic antagonists (LAMA, e.g., tiotropium)7 days
  • Inhaled corticosteroids, leukotriene blockers, and antihistamines do not significantly affect the test acutely — continue these. Withdrawing ICS also carries its own risk for asthma patients.
  • Practical tip: Spell out exactly what to hold and when — for both the patient and the PFT lab — at the time the test is ordered.

Interpreting Results

Negative Test (PC20 > 16 mg/mL)

  • Very high negative predictive value in symptomatic adults.
  • Makes current asthma quite unlikely (assuming proper test conduct).
  • This is the test’s greatest strength: it is an excellent rule-out test.

Positive Test (PC20 ≤ 8–16 mg/mL)

  • More nuanced — airway hyperresponsiveness is not unique to asthma.
  • Can be positive in: chronic cough, allergic rhinitis, COPD, and even some healthy asymptomatic individuals.
  • A positive result raises probability but must be interpreted alongside the clinical story, variable respiratory symptoms, peak flow variability, FeNO, and ICS response.

Safety and Risks

  • Overall, the test is quite safe; significant adverse effects are rare.
  • Temporary breathing discomfort is expected (bronchoconstriction is being induced).
  • Severe bronchospasm is possible:
    • A trained clinician should be available; SABA inhaler/nebulizer must be immediately on hand; a physician should be reachable in the facility.
  • Contraindications / cautions:
    • Avoid if FEV1 < 70% predicted or < 1–1.5 L (baseline obstruction greatly increases risk).
    • Avoid within 3 months of an acute cardiac event (rare risk of cardiac events with unstable cardiac disease).

Five Pearls — Quick Recap

  1. What it tests: Methacholine challenge is a direct test of AHR with high specificity but variable sensitivity — it belongs inside a diagnostic pathway, not as a standalone asthma test.
  2. When to use it: Most useful for symptomatic patients with normal spirometry and no bronchodilator response, after FeNO and peak flow variability have been considered.
  3. Technique and meds matter: Use tidal breathing protocol; respect washout intervals — especially the 7-day LAMA washout and 24–48 hour LABA window — to avoid false negatives.
  4. Safety: Generally safe, but can induce significant bronchoconstriction. Have a SABA available and avoid the test in patients with FEV1 < 70% predicted.
  5. Interpretation: A negative test (PC20 > 16 mg/mL) strongly argues against current asthma. A positive test raises probability but is not specific — interpret alongside the full clinical picture.
  1. Coates AL, Wanger J, Cockcroft DW, Culver BH; Bronchoprovocation Testing Task Force: Kai-Håkon Carlsen; Diamant Z, Gauvreau G, Hall GL, Hallstrand TS, Horvath I, de Jongh FHC, Joos G, Kaminsky DA, Laube BL, Leuppi JD, Sterk PJ. ERS technical standard on bronchial challenge testing: general considerations and performance of methacholine challenge tests. Eur Respir J. 2017 May 1;49(5):1601526. doi: 10.1183/13993003.01526-2016. PMID: 28461290.
  2. Lee, J., & Song, J. U. (2021). Diagnostic comparison of methacholine and mannitol bronchial challenge tests for identifying bronchial hyperresponsiveness in asthma: a systematic review and meta-analysis. Journal of Asthma, 58(7), 883–891. https://doi.org/10.1080/02770903.2020.1739704
  3. Davis BE, Blais CM, Cockcroft DW. Methacholine challenge testing: comparative pharmacology. J Asthma Allergy. 2018 May 14;11:89-99. doi: 10.2147/JAA.S160607. PMID: 29785128; PMCID: PMC5957064.

117. Pulm PEEPs Pearls: Spontaneous Breathing Trials

PPP Cover Images

This week’s Pulm PEEPs Pearls episode is all about spontaneous breathing trials (SBTs). SBTs are a standard part of the daily practice in the intensive care unit, but the exact methods vary across ICUs and institutions. Listen in to hear about the most common methods of SBTs, the physiology of each method, and what the evidence says.

This episode was prepared with research by Pulm PEEPs Associate Editor George Doumat.

Dustin Latimer, another Pulm PEEPs Associate Editor, assisted with audio and video editing.

  1. What an SBT is really testing
  • An SBT is a stress test for post-extubation work of breathing, not just a ventilator check.
  • The goal is to balance sensitivity and specificity:
    • Too hard → unnecessary failures and delayed extubation
    • Too easy → false positives and higher risk of reintubation
  1. Common SBT modalities and how they compare
  • T-piece
    • No inspiratory support and no PEEP
    • Highest work of breathing
    • Most “physiologic” but often too strict
  • Pressure support (PS) + PEEP (e.g., 5/5 or 8/5)
    • Offsets ETT resistance and provides modest assistance
    • Easier to pass than T-piece
  • CPAP (0/5)
    • No inspiratory help, but provides PEEP to counter ETT resistance
    • Sits between PS and T-piece in difficulty
  1. Evidence favors pressure-supported SBTs for most patients
  • Large meta-analysis (~6,000 patients, >40 RCTs):
    • Pressure-supported SBTs increase successful extubation (~7% absolute benefit)
    • No increase in reintubation rates
  • Trials (e.g., FAST trial):
    • Patients pass SBTs earlier
    • Leads to earlier extubation and fewer ventilator-associated risks
  • Bottom line: A 30-minute PS 5/5 SBT is evidence-based and appropriate for most stable ICU patients
  1. When a T-piece still makes sense

T-piece SBTs are useful when:

  • Cost of reintubation is high
    • Difficult airway
    • Prior failed extubation
  • Pretest probability of success is low
    • Prolonged or difficult weaning
    • Tracheostomy vs extubation decisions
  • Need to mimic physiology without positive pressure
    • In LV dysfunction or pulmonary edema even small amounts PEEP may significantly improve physiology
  • Some centers use a hybrid approach: PS SBT → short confirmatory T-piece before extubation
  1. CPAP as a middle ground
  • Rationale:
    • Allows full patient effort while compensating for ETT resistance
  • Evidence:
    • Fewer and smaller trials
    • Possible modest improvement in extubation success
    • No clear mortality or LOS benefit
  • Reasonable option based on patient physiology, institutional protocols, and clinician comfort
  1. No single “perfect” SBT mode
  • Across PS, T-piece, CPAP, and newer methods (e.g., high-flow via ETT) there are no consistent differences in mortality or length of stay
  • What matters most:
    • Daily protocolized screening
    • Thoughtful bedside clinical judgment
    • Matching SBT difficulty to patient-specific risk
  1. Institutional variation is normal—and acceptable
  • Examples:
    • PS 10/5 in postoperative surgical ICU patients
    • PS 5/0 as an intermediate difficulty option
  • Key question clinicians should ask: What does passing or failing this specific SBT tell me about this patient’s likelihood of post-extubation success?
  1. Take-home pearls
  1. SBTs are stress tests of post-extubation physiology.
  2. PS 5/5 for 30 minutes is a strong default for most ICU patients.
  3. T-piece trials are valuable when false positives are costly or physiology demands it.
  4. CPAP is reasonable but supported by less robust data.
  5. Consistency, daily screening, and judgment matter more than the exact mode.

  • Burns KEA, Khan J, Phoophiboon V, Trivedi V, Gomez-Builes JC, Giammarioli B, Lewis K, Chaudhuri D, Desai K, Friedrich JO. Spontaneous Breathing Trial Techniques for Extubating Adults and Children Who Are Critically Ill: A Systematic Review and Meta-Analysis. JAMA Netw Open. 2024 Feb 5;7(2):e2356794. doi: 10.1001/jamanetworkopen.2023.56794. PMID: 38393729; PMCID: PMC10891471.
  • Burns KEA, Sadeghirad B, Ghadimi M, Khan J, Phoophiboon V, Trivedi V, Gomez Builes C, Giammarioli B, Lewis K, Chaudhuri D, Desai K, Friedrich JO. Comparative effectiveness of alternative spontaneous breathing trial techniques: a systematic review and network meta-analysis of randomized trials. Crit Care. 2024 Jun 8;28(1):194. doi: 10.1186/s13054-024-04958-4. PMID: 38849936; PMCID: PMC11162018.
  • Subirà C, Hernández G, Vázquez A, Rodríguez-García R, González-Castro A, García C, Rubio O, Ventura L, López A, de la Torre MC, Keough E, Arauzo V, Hermosa C, Sánchez C, Tizón A, Tenza E, Laborda C, Cabañes S, Lacueva V, Del Mar Fernández M, Arnau A, Fernández R. Effect of Pressure Support vs T-Piece Ventilation Strategies During Spontaneous Breathing Trials on Successful Extubation Among Patients Receiving Mechanical Ventilation: A Randomized Clinical Trial. JAMA. 2019 Jun 11;321(22):2175-2182. doi: 10.1001/jama.2019.7234. Erratum in: JAMA. 2019 Aug 20;322(7):696. doi: 10.1001/jama.2019.11119. PMID: 31184740; PMCID: PMC6563557.
  • Burns KEA, Wong J, Rizvi L, Lafreniere-Roula M, Thorpe K, Devlin JW, Cook DJ, Seely A, Dodek PM, Tanios M, Piraino T, Gouskos A, Kiedrowski KC, Kay P, Mitchell S, Merner GW, Mayette M, D’Aragon F, Lamontagne F, Rochwerg B, Turgeon A, Sia YT, Charbonney E, Aslanian P, Criner GJ, Hyzy RC, Beitler JR, Kassis EB, Kutsogiannis DJ, Meade MO, Liebler J, Iyer-Kumar S, Tsang J, Cirone R, Shanholtz C, Hill NS; Canadian Critical Care Trials Group. Frequency of Screening and Spontaneous Breathing Trial Techniques: A Randomized Clinical Trial. JAMA. 2024 Dec 3;332(21):1808-1821. doi: 10.1001/jama.2024.20631. PMID: 39382222; PMCID: PMC11581551.
  • Mahul M, Jung B, Galia F, Molinari N, de Jong A, Coisel Y, Vaschetto R, Matecki S, Chanques G, Brochard L, Jaber S. Spontaneous breathing trial and post-extubation work of breathing in morbidly obese critically ill patients. Crit Care. 2016 Oct 27;20(1):346. doi: 10.1186/s13054-016-1457-4. PMID: 27784322; PMCID: PMC5081985.
  • Yi LJ, Tian X, Chen M, Lei JM, Xiao N, Jiménez-Herrera MF. Comparative Efficacy and Safety of Four Different Spontaneous Breathing Trials for Weaning From Mechanical Ventilation: A Systematic Review and Network Meta-Analysis. Front Med (Lausanne). 2021 Nov 22;8:731196. doi: 10.3389/fmed.2021.731196. PMID: 34881255; PMCID: PMC8647911.​